Antibiotic
An antibiotic is a type of medicine that fights germs called bacteria. It is the most important kind of antibacterial agent for fighting bacterial infections. Antibiotic medications are widely used for treatment and prevention of these infections. Antibiotics can either kill bacteria or inhibit the growth of them. A few antibiotics also work against some tiny single-celled organisms, but they do not work against viruses or fungi.
The word "antibiotic" comes from Greek roots that mean "opposing life." Some people use the word for any substance used against microbes. In medical use, though, antibiotics such as penicillin are made naturally, when one microorganism fights another. Other antibacterials, such as sulfonamides and antiseptics, are fully synthetic, meaning they are made by people. Both kinds stop microorganisms from growing or kill them, so both are part of antimicrobial chemotherapy.
Antibacterials include bactericides, bacteriostatics, antibacterial soaps, and chemical disinfectants. Antibiotics are a special group of these that are used more specifically in medicine, and sometimes in livestock feed.
This article is about antibiotics used to treat bacterial infections. The word "Antibacterial" can also lead to other uses, see Antibacterial (disambiguation). For anti-tumor antibiotics, see Chemotherapy § Cytotoxic antibiotics.
Early history
The earliest known use of antibiotics was found in northern Sudan. Ancient people there, as early as 350 to 550 CE, ate antibiotics as part of their diet. Chemical tests on Nubian skeletons show high, steady levels of tetracycline, a strong antibiotic. Researchers think these people brewed drinks from grain fermented with Streptomyces, a bacterium that naturally makes tetracycline.
Given the amount of tetracycline there, they had to know what they were doing.
— George J. Armelagos, biological anthropologist
Other ancient peoples, including those in Egypt, China, Serbia, Greece, and Rome, later used moldy bread on infections. The first person to write down the use of molds to treat infections was John Parkinson (1567–1650). Antibiotics changed medicine in the 20th century. Work on antibacterial drugs began in Germany with Paul Ehrlich in the late 1880s. Alexander Fleming (1881–1955) discovered modern penicillin in 1928, and its wide use was very helpful during wartime. A team led by Gerhard Domagk developed the first sulfonamide and the first systemically active antibacterial drug, Prontosil, in 1932 or 1933 at the Bayer Laboratories of the IG Farben company in Germany. Today, antibiotics are sometimes overused, and some bacteria have become resistant to them. This antimicrobial resistance (AMR) is a natural process, but it is mainly caused by misusing and overusing these medicines. At the same time, many people around the world cannot get the medicines they need. The World Health Organization calls AMR a serious threat that is happening right now in every region of the world. Each year, nearly 5 million deaths are linked to AMR, and about 1.27 million deaths in 2019 were directly caused by it.
Etymology
The French scientist Jean Paul Vuillemin introduced the term "antibiosis," which means "against life." He used it to describe what these early antibacterial drugs did. In 1877, Louis Pasteur and Robert Koch saw that an airborne bacillus could slow the growth of Bacillus anthracis. Later, in 1947, Selman Waksman, an American microbiologist, renamed these drugs antibiotics.
The word antibiotic was first used in 1942 by Selman Waksman and his team in journal articles. It described any substance made by a microorganism that could stop other microorganisms from growing. This meant that substances such as gastric juices and hydrogen peroxide, which kill bacteria but are not made by microorganisms, were left out. Man-made compounds like the sulfonamides were also left out. Today, "antibiotic" is used for any medicine that kills bacteria or stops them from growing, whether or not a microorganism made it. The word comes from Latin and Greek roots meaning "against" and "life," and "antibacterial" comes from Greek words meaning "against" and "staff, cane," because the first bacteria discovered were rod-shaped.
Usage
Antibiotics are used to treat or prevent bacterial infections and sometimes protozoan infections, since metronidazole is effective against some parasitic diseases. When doctors think an infection is causing an illness but have not yet found the germ responsible, they use empiric therapy. This means giving a broad-spectrum antibiotic based on the signs and symptoms, while laboratory results, which can take several days, are awaited. Once the germ is known, definitive therapy can start, usually with a narrow-spectrum antibiotic. Cost also affects the choice. Knowing the germ can lower cost and toxicity and reduce the chance of antimicrobial resistance. To avoid surgery, antibiotics may be given for non-complicated acute appendicitis.
Antibiotics may also be given as a preventive measure, usually for people at risk, such as those with a weakened immune system (especially HIV cases, to prevent pneumonia), those taking immunosuppressive drugs, cancer patients, and people having surgery to help prevent infection of incisions. They are also important in dental antibiotic prophylaxis, where they may prevent bacteremia and infective endocarditis, and they are used to prevent infection in neutropenia, particularly cancer-related. Antibiotics are usually taken by mouth, but in more serious illness they can be given intravenously or by injection. They can also be applied topically, such as eye drops for conjunctivitis or ear drops for ear infections. Antibiotic use differs greatly between countries. A WHO report published in 2018 looked at 2015 data from 65 countries. Mongolia had the highest rate, and Burundi had the lowest. Amoxicillin and amoxicillin/clavulanic acid were the most frequently used.
Side effects
Antibiotics are checked for harmful effects before they are approved for use, and they are usually considered safe and well tolerated. However, some antibiotics have been linked to many side effects, which can range from mild to very severe. This depends on the type of antibiotic, the microbes it targets, and the individual patient. Side effects may come from how the medicine works in the body or how it affects the body, or they may be allergic reactions. They can range from fever and nausea to major allergic reactions, including photodermatitis and anaphylaxis.
Common side effects of antibiotics taken by mouth include diarrhea. This happens when the mix of bacteria in the intestinal flora is disrupted, which can let harmful bacteria such as Clostridioides difficile grow too much. Taking probiotics during antibiotic treatment can help prevent this kind of diarrhea. Antibiotics can also affect the vaginal flora and may lead to too much growth of yeast of the genus Candida in the vulvo-vaginal area. Side effects can also come from interaction with other medicines, such as the possibility of tendon damage when a quinolone antibiotic is given with a systemic corticosteroid. Some antibiotics may also damage the mitochondrion, a part of cells that came from bacteria and is found in human and other similar cells. This damage causes oxidative stress in cells and has been suggested as a reason for side effects from fluoroquinolones. Antibiotics can also damage the endoplasmic reticulum, and they are known to affect chloroplasts.
Interactions
Few well-controlled studies show whether antibiotic use increases the risk of oral contraceptive failure. Most studies indicate that antibiotics do not interfere with birth control pills. Clinical studies suggest that the failure rate of contraceptive pills caused by antibiotics is very low, about 1%. Missing a pill (non-compliance), vomiting, or diarrhea may raise the risk, as may stomach problems or differences between people in how well the pill is absorbed, which can change ethinylestradiol serum levels in the blood. Women with menstrual irregularities may be at higher risk and should use backup contraception during antibiotic treatment and for one week after it ends. For the broad-spectrum antibiotic rifampicin, reported effects may be due to liver enzymes breaking down the pill's active ingredients more quickly. Effects on the intestinal flora, which might reduce the absorption of estrogens in the colon, have also been suggested, but these ideas are inconclusive and controversial. Clinicians have recommended extra contraceptive measures during treatment with antibiotics that may interact with contraceptives, and more studies are needed.
Alcohol and certain antibiotics may interact, causing side effects and reducing how well the treatment works. Moderate drinking is unlikely to interfere with many common antibiotics, but some types can cause serious side effects when mixed with alcohol, so the risk depends on the type of antibiotic. Antibiotics such as metronidazole, tinidazole, cephamandole, latamoxef, cefoperazone, cefmenoxime, and furazolidone cause a disulfiram-like chemical reaction with alcohol by blocking the enzyme acetaldehyde dehydrogenase, which may lead to vomiting, nausea, and shortness of breath. Alcohol may also reduce the effectiveness of doxycycline and erythromycin succinate, and it can change how the liver breaks down antibiotic compounds.
Pharmacodynamics
Main article: Antimicrobial pharmacodynamics
How well treatment with antibacterial medicines works depends on several things. These include host defense mechanisms, where the infection is, and how the medicine moves through and acts in the body (pharmacokinetic and pharmacodynamic properties). Whether an antibacterial kills bacteria may depend on the stage of bacterial growth, and it often needs the bacteria to be active and dividing. Laboratory studies show this, and in clinical settings it has also been shown to clear bacterial infections. Because an antibacterial's effect often depends on its strength, scientists usually measure the minimum inhibitory concentration and minimum bactericidal concentration. To predict how a patient will do, the medicine's effect is usually considered together with its pharmacokinetic profile.
In serious infections, including tuberculosis, doctors may use combination therapy, which means giving two or more antibiotics at the same time. This has been used to delay or prevent resistance. In acute bacterial infections, antibiotics in combination are chosen for their synergistic effects, meaning the two together work better than either one alone. Fosfomycin has the most synergistic combinations among antibiotics and is almost always used as a partner drug. Combination therapy also widens the range of bacteria that are targeted, so at least one antibiotic is likely to work, which matters most when the cause of infection is unknown. Methicillin-resistant Staphylococcus aureus infections may be treated with fusidic acid and rifampicin together. Some antibiotics given together can work against each other, so the combined effect may be weaker than using one alone (monotherapy). For example, chloramphenicol and tetracyclines work against penicillins. This can vary depending on the type of bacteria. In general, combining a bacteriostatic antibiotic with a bactericidal antibiotic makes them work against each other. Antibiotics are also sometimes given with resistance-modifying agents. For example, β-lactam antibiotics may be used with β-lactamase inhibitors, such as clavulanic acid or sulbactam, when a patient has an infection caused by bacteria that produce β-lactamase.
Classes
For a more comprehensive list, see List of antibiotics.
Antibiotics are sorted into groups based on their mechanism of action, their chemical structure, or their spectrum of activity. Most of them work by targeting bacterial functions or growth. Some groups, such as penicillins and cephalosporins, attack the bacterial cell wall. Polymyxins target the cell membrane. Rifamycins, lipiarmycins, quinolones, and sulfonamides interfere with important bacterial enzymes. These groups are bactericidal, which means they kill bacteria.
Protein synthesis inhibitors, including macrolides, lincosamides, and tetracyclines, usually stop bacteria from growing further. They are bacteriostatic, except for the bactericidal aminoglycosides. Antibiotics can also be grouped by their target. "Narrow-spectrum" antibiotics work on specific types of bacteria, such as gram-negative or gram-positive bacteria, while broad-spectrum antibiotics affect a wide range of bacteria. After a 40-year break in finding new classes of antibacterial compounds, four new classes were introduced for clinical use in the late 2000s and early 2010s: cyclic lipopeptides (such as daptomycin), glycylcyclines (such as tigecycline), oxazolidinones (such as linezolid), and lipiarmycins (such as fidaxomicin).
Production
Main article: Production of antibiotics
As medicine science has improved, most modern antibacterials are semisynthetic changes made to natural compounds. Examples include the beta-lactam antibiotics, such as the penicillins (made by fungi in the genus Penicillium), the cephalosporins, and the carbapenems. Some antibacterials are still taken from living organisms, such as the aminoglycosides. Others, like the sulfonamides, the quinolones, and the oxazolidinones, are made only through chemical synthesis. Many of these medicines are small molecules with a molecular weight of less than 1000 daltons.
Since the early work of Howard Florey and Chain in 1939, antibiotics have become very important to medicine, which has led to much research into making antibacterials on a large scale. After testing antibacterials against many kinds of bacteria, the active compounds are produced using fermentation, usually in conditions with plenty of oxygen.
Resistance
Main article: Antimicrobial resistance
Antimicrobial resistance (AMR) is a natural process. It is mostly driven by the misuse and overuse of antimicrobials, even though many people around the world cannot get the medicines they need. Resistance often grows through evolutionary processes during antibiotic treatment, which can select for bacteria that survive high doses. This was shown in 1943 by the Luria–Delbrück experiment. Penicillin and erythromycin used to work well against many bacteria, but they have become less effective. Resistance can spread through horizontal gene transfer, which is more likely where antibiotics are used often. Resistance can also reduce the fitness of bacteria, though extra mutations may help them survive. Resistance can come from a target missing from the bacterial genome, or from a mutation or extra DNA. Resistance genes can move between bacteria on plasmids. Each year, nearly 5 million deaths are linked to AMR, and antibiotic-resistant bacteria are a threat to health around the world. Some resistant strains, called "superbugs," have made diseases that were once well controlled harder to treat. Each year, nearly half a million new cases of multidrug-resistant tuberculosis (MDR-TB) are estimated to occur. The NDM-1 enzyme helps bacteria resist a broad range of beta-lactam antibiotics. The UK's Health Protection Agency said that most bacteria with NDM-1 are resistant to all standard intravenous antibiotics for severe infections. In 2016, an E. coli superbug resistant to colistin, "the last line of defence" antibiotic, was found in the United States. Even Bacteroides bacteria, which were once seen as less of a concern, now show high resistance rates.
Misuse also plays a large part. Antibiotics are sometimes used for viral infections like the common cold, which they cannot treat, and some are prescribed to people who expect them. Overuse can harm critically ill patients in Intensive care units, and self-prescribing is one example of misuse. Other forms include prophylactic use in travelers, using the wrong dose, and not finishing a course of treatment. Studies of respiratory tract infections and common misconceptions about antibiotics show that they can contribute to overuse. Several groups, including the Centers for Disease Control and Prevention, the National Institutes of Health, the National Academy of Sciences, the U.S. Food and Drug Administration, the American Medical Association, the American Public Health Association, and the Natural Resources Defense Council, have worked to limit unnecessary use, including in use of antibiotics in livestock. Antibiotics can also cause harm such as anaphylaxis, drug toxicity, and Clostridioides difficile associated diarrhoea. They can affect mitochondrial function, the microbiome of the body, immune cells, and sepsis. Antibiotics can save lives, but using them too often can cause harm.
History
Before the early 20th century, treatments for infections were based mainly on medicinal folklore. Mixtures with antimicrobial properties were described over 2,000 years ago. Many ancient cultures, including the ancient Egyptians and ancient Greeks, used carefully chosen mold and plant materials to treat infections. Nubian mummies studied in the 1990s were found to contain tetracycline. For a chronological guide, see Timeline of antibiotics. Modern antibiotic medicine began with synthetic antibiotics made from dyes. In Germany, Paul Ehrlich began this work in the late 1880s. In 1907, he discovered salvarsan, the first synthetic antibacterial organoarsenic compound, now called arsphenamine. In 1908, Ehrlich received the Nobel Prize in Physiology or Medicine.
The first sulfonamide, Prontosil, was developed by a team led by Gerhard Domagk in the early 1930s at the Bayer Laboratories in Germany. Domagk received the 1939 Nobel Prize in Physiology or Medicine for this work. In 1928, Alexander Fleming noticed that a green mold killed bacteria in one of his culture plates, and he named the substance penicillin. In 1942, Ernst Chain, Howard Florey, and Edward Abraham succeeded in purifying the first penicillin, penicillin G. Chain, Florey, and Fleming shared the 1945 Nobel Prize in Medicine for penicillin. During the mid-20th century, many new antibiotics were introduced. From 1935 to 1968, 12 new classes were launched, but only two new classes were introduced between 1969 and 2003.
See also: History of penicillin
Antibiotic pipeline
Experts from the WHO and the Infectious Disease Society of America report that the supply of new antibiotics is weak. Bacteria are getting better at developing resistance, and the number of new antibiotics approved each year has been falling. Seven antibiotics against Gram-negative bacilli were in phase 2 or phase 3 clinical trials, but these drugs do not cover all forms of resistance. As of May 2017, the WHO counted fifty-one new antibiotics, including combinations, in phase 1 to 3 trials. Antibiotics against multidrug-resistant Gram-positive germs remain a high priority. In the US, the Antibiotic Development to Advance Patient Treatment (ADAPT) Act was introduced to speed up the development of antibiotics against dangerous "superbugs," and the CDC would monitor antibiotic use and resistance.
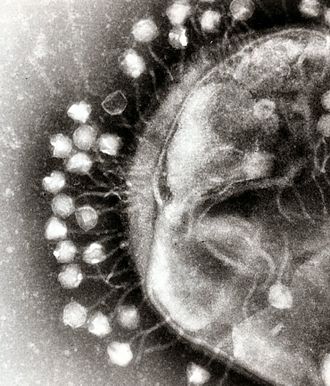
Because resistant bacteria keep appearing and spreading, scientists are always looking for new treatments. Some approaches use natural sources, and others use newer chemistry or biology. Examples include phage therapy, fecal microbiota transplants, antisense RNA, and CRISPR-Cas9. Reducing the pressure that helps resistance spread is also important, and vaccines play an essential role because they prevent infections and reduce the need for antibiotics.

Quiz time!
5 questions about Antibiotic
What kind of germs do antibiotics fight?
Pictures
Keep exploring




This article is a child-friendly adaptation of the Wikipedia article on Antibiotic, available under CC BY-SA 4.0.
Images from Wikimedia Commons. Tap any image to view credits and license.